Hypersensitivity and allergic disorders, psychiatric disorders, neurological disorders, infections, immunological and inflammatory disorders, type 1 diabetes (T1D), type 2 diabetes (T2D), ocular disorders, skeletal disorders, and malignancies were conditions that were analyzed individually.
The authors wrote, “descriptive statistics were computed for patients at risk, stratified by severity and compared with the non-AD reference cohort as mean and standard deviation (SD) for continuous variables and number and percentage for categorical variables.”
Cumulative incidence curves, forest plots, and analysis using Cox proportional hazards models displayed the association between time to the start of a clinically managed condition and the presence of AD.
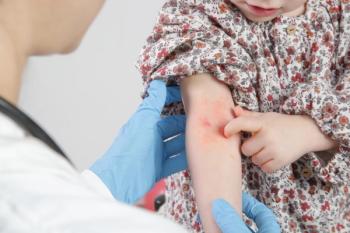
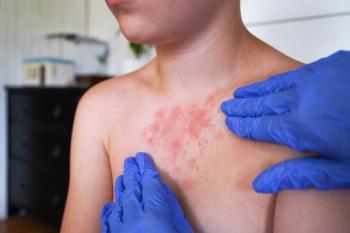
There were 165,145 patients in the AD cohort, of which 120,684 (73%) were classified with M2M disease (mean age of 4.64 years; 47.25% females) and 44,461 (27%) were classified with severe AD (mean age of 7.52 years; 48.01% females).
At baseline, the greatest differences in prevalence of conditions were observed for hypersensitivity, allergic disorders, and infections, all of which were higher in the AD cohort compared to the non-AD reference cohort.
In the AD cohort, less than 20% of patients used systemic treatments during follow-up, while approximately 50% of these patients received their first systemic treatments before age 7 years.
Of patients in the AD cohort, 36.6% developed at least 1 comorbidity amid follow-up compared to 28.5% in the non-AD reference cohort, and “of those patients who developed at least [1] comorbidity, 27.1% and 19.7% developed multiple comorbidities (≥2) in the AD cohort and the non-AD reference cohort, respectively,” the investigators wrote.
Occurring in 18.55% of patients in the AD cohort (95% CI, [18.312%-18.80%]) and 10.03% of patients in the non-AD reference cohort (95% CI [9.88%-10.18%]), hypersensitivity and allergic disorders were the most common comorbidities.
Infections were the second most common comorbidities in the AD cohort, occurring in 18.35% (18.12%-18.59%) of patients in the AD cohort and 5.29% (5.18%-5.41%) in the non-AD reference cohort.
The third most common comorbidity between groups was skeletal disorders, occurring in 13.20% (13.02%-13.39%) of patients in the AD cohort, compared to 9.65% (9.51%-9.80%) in the non-AD reference cohort.
Except for T1D and skeletal disorders, compared with the reference cohort, patients with AD displayed a higher risk of developing comorbid conditions for all investigated categories.
Compared to the reference group, the highest risk was observed for hypersensitivity and allergic disorders (hazard ratio [HR]: 3.87). Malignancies, with a HR of 2.53, and immunological and inflammatory disorders (HR: 2.36) followed.
Comorbidity onset increased with AD severity, and those with AD had a higher risk of developing multiple comorbidities. Compared to patients in remission, the investigators concluded that those with active AD were associated with increased risk of comorbidity.
Reference:
Kobyletzki L, Henrohn D, Ballardini N, et al. Comorbidities in childhood atopic dermatitis: A population‐based study. Acad Dermatol Venereol. Published online October 22, 2023:jdv.19569. doi:10.1111/jdv.19569